New ADA guidelines highlight best practices in oral cancer detection
The American Dental Association has released updated clinical guidelines to help dental professionals detect oral cancer.1 Through routine screenings and thorough examinations, dental professionals are uniquely positioned to catch early signs in patients.
The American Cancer Society projects 60,480 new cases of oral cavity and oropharyngeal cancer and 13,150 deaths in 2026. The ADA’s updated guidelines focus more narrowly on oral cavity cancer, with an estimated 38,720 new cases and 8,390 deaths expected in 2026.2
Following the updated guidelines can help clinicians focus on evidence-based detection methods, recognize when further evaluation is necessary, and avoid relying on adjunctive tools that have not demonstrated sufficient clinical benefit. As stated by the associate director of health care guidelines at the Center for Integrative Global Oral Health in an ADA press release: “Getting emerging evidence into the hands of clinicians quickly can be the difference between early detection of oral cancer and a late-stage diagnosis.”1
What the guidelines recommend
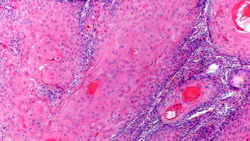
The ADA’s new guidelines are an updated version of their guidelines from 2017 on the evaluation of potentially malignant disorders, including oral cancer, and the first fully developed under the 2025 ADA Living Guideline Program. Per the updated guidelines, regular dental exams are essential, acting as the first step in cancer detection. If a lesion is detected, conducting a biopsy is the only definitive way to confirm the diagnosis of oral potentially malignant disorders (OPMDs) and oral and lip squamous cell carcinomas (OSCCs).
The ADA also stresses good follow-up practices, noting that, “clinicians should recommend biopsy or referral when oral mucosal abnormalities are not resolving beyond 10 to 14 days after initial evaluation without a definitive diagnosis or treatment plan.” When determining whether a biopsy or specialist referral is necessary for an adult patient with oral lesions, or to screen patients without visible lesions, the ADA advises against commercially available cytology (which can still be useful in some cases), light-based vital staining, and salivary adjunct tests.1
Commercially available cytology is the examination of loose cells. However, experts note that cytology can still be advantageous when biopsy “is not possible, advisable, or indicated, particularly for lesions that could be cause for concern.” Additionally, “salivary adjunct tests are recommended only for use in research settings.”
Light-based and vital staining are used to highlight abnormal areas in the mouth. For vital staining, experts say toluidine blue should not be used as an adjunct for patients with any mucosal abnormality in the oral cavity or on the lip. It is also not recommended for asymptomatic patients with no clinically evident oral mucosal abnormalities.
According to the ADA, salivary adjunct tests for adults with or without visible lesions should only be used for research purposes.
Other clinical considerations for oral cancer detection
When conducting oral cancer screenings, dental professionals can also include a review of patients’ lifestyle habits that may increase their risk for developing an oral lesion. Considerations include:
-
tobacco/smokeless use
-
alcohol use
-
precancerous lesions
-
field cancerization
-
genetics
-
gender
-
UV light
-
increased body mass index
-
improper nutrition3
Before performing a clinical oral examination (COE), clinicians should obtain an up-to-date medical, social, and dental history from their patients. They should also explain why they’re conducting the exam and how it can help them spot mucosal abnormalities, including ones that are potentially malignant.
Clinicians should also stress the importance of contacting a dental or medical professional if a patient notices an unusual lump or spot in their mouth, especially one that doesn’t seem to heal. “Let your dentist or physician know, especially if you also notice bleeding, pain, difficulty swallowing, or hoarseness,” advises Dr. Alessandro Villa, chief of oral medicine, oral oncology and dentistry at Herbert Wertheim Cancer Institute. “If something looks concerning, your dentist may obtain a biopsy.”1
For clinicians, early detection requires more than simply looking for an obvious lesion. A thorough patient history, consistent clinical examination, appropriate follow-up, and timely referral or biopsy can all play a role in identifying concerning changes earlier.
References:
-
Dental examinations crucial in early oral cancer detection. American Dental Association. Press release. September 29, 2026.
-
Bhosale AS, Martins-Pfeifer C, Verdugo-Paiva, et al. Living evidence-informed guideline on the early detection of oral squamous cell carcinoma and potentially malignant disorders: light-based adjuncts to determine the need for biopsy, Version 2026 1.0. J Am Dent Assoc. 2026;157(9):968-979. doi:10.1016/j.adaj.2026.04.010
-
Brown S. Your role in oral cancer screening: When, how, and why. RDH. February 13, 2023. https://www.rdhmag.com/patient-care/video/14288997/your-role-in-oral-cancer-screening-when-how-and-why
About the Author
 Sarah Butkovic, MA, BA
Sarah Butkovic, MA, BA, is an Associate Editor at Endeavor Business Media, where she works on creating and editing engaging and informative content for today's leading online dentistry publications. She holds a Master's English Language and Literature from Loyola University Chicago and is passionate about producing high-quality content that educates, inspires, and connects with readers.